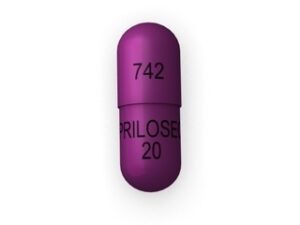
Rabeprazole (Rabeprazole Sodium) – Patient Guide (Australia)
Rabeprazole (rabeprazole sodium) is a medicine from the proton pump inhibitor (PPI) family. It reduces stomach acid production and is commonly used to treat conditions such as reflux (heartburn/GERD) and ulcer disease. This guide explains how rabeprazole works, when to take it, key interactions, typical dosing, practical tips, and what to expect for safety and effectiveness in Australia.
Basic product information
- Medicine name: Rabeprazole (rabeprazole sodium)
- Drug class: Proton pump inhibitor (PPI)
- Common forms: Delayed-release tablets/capsules (brand and strengths vary)
- Typical strengths: Often 10 mg or 20 mg (depending on indication and product)
- How it works: Blocks an enzyme involved in acid production in the stomach lining
Availability in Australia depends on the product brand and strength. Some rabeprazole products may be listed on the Australian Register of Therapeutic Goods (ARTG) and supplied through pharmacies, with dosing tailored to the condition being treated.
How rabeprazole works (mechanism of action)
Rabeprazole is a proton pump inhibitor. In the stomach, specialised cells (parietal cells) produce acid using tiny “pumps” called proton pumps (H+/K+ ATPase). Rabeprazole works by irreversibly inhibiting these pumps, leading to a reduction in gastric acid secretion.
Because it targets the acid-producing mechanism at the cellular level, rabeprazole can provide sustained acid suppression across the day. Unlike antacids that neutralise existing acid, PPIs help prevent new acid production, which is why they are often preferred for healing and long-term control of reflux-related symptoms.
Pharmacokinetics (how the body processes rabeprazole)
While individual response can vary, the overall pattern is consistent:
- Absorption: Rabeprazole is absorbed after oral dosing. Because it is designed to be “acid-protected” (delayed/enteric release), it typically remains stable until it reaches the intestines for absorption.
- Onset: Many people notice symptom improvement within a day or two, but optimal acid control and healing may take several days of consistent use.
- Peak effect: Acid suppression increases as the medicine reaches its target pumps; repeated daily dosing often improves effectiveness.
- Metabolism: Rabeprazole is metabolised in the liver primarily through enzymatic pathways (including CYP systems), then converted to inactive metabolites.
- Excretion: Metabolites are eliminated mainly via the kidneys and through bile/intestinal routes.
Why timing matters: For PPIs, consistency is important. The medication works best when taken correctly before meals so it can reach active form in time to inhibit pumps that are stimulated by food.
Typical uses in Australia (indications)
Rabeprazole is used for a range of acid-related gastrointestinal conditions, including:
- Gastro-oesophageal reflux disease (GERD) and reflux symptoms (heartburn, regurgitation)
- Erosive oesophagitis (inflammation/erosions of the oesophagus due to acid reflux)
- Gastric and duodenal ulcer disease (including prevention of recurrence in appropriate cases)
- Helicobacter pylori–related disease (often as part of combination therapy with antibiotics and other medicines, where applicable)
- Zollinger–Ellison syndrome (rare condition with excessive stomach acid production)
The exact indication and dose depend on the diagnosis, severity, and local treatment plan.
How to take rabeprazole: timing and practical guidance
Best time to take it
Rabeprazole is usually taken once daily (sometimes twice daily depending on the condition). A common practical recommendation is:
- Take it before food, ideally 30 minutes before breakfast.
- If your product instructions differ, follow the label guidance or your healthcare professional’s direction.
Taking the dose before a meal helps ensure that the acid pumps are “switched on” by food and then inhibited by the medicine at the right time.
If you miss a dose
- Take it as soon as you remember.
- If it is almost time for your next dose, skip the missed dose.
- Do not take a double dose to make up for the missed tablet.
Practical use tips
- Swallow whole: Do not crush or chew unless the product leaflet specifies otherwise.
- Be consistent: Take at the same time each day.
- Allow time: If you are treating reflux or healing oesophagitis, symptoms may improve in days, but complete healing can take longer.
- Do not stop suddenly without a plan: Long-term use may require gradual review with your clinician.
Dosing overview (general guidance)
Dosing depends on the specific condition, severity, and product strength. Below is a general, patient-friendly overview. Always follow the dosing instructions on the product pack or those provided for your situation.
| Condition (examples) | Typical rabeprazole dose | Notes |
|---|---|---|
| Heartburn / GERD | Often 10 mg once daily or 20 mg once daily (varies) | For symptom control, effectiveness depends on correct timing before meals. |
| Erosive oesophagitis (healing) | Often 20 mg once daily (varies by case) | Healing may take several weeks; symptom relief may occur earlier. |
| Gastric/duodenal ulcers | Often 20 mg once daily (sometimes adjusted) | Ulcer treatment schedules can vary; follow the planned course. |
| Maintenance / recurrence prevention | Often 10 mg or 20 mg daily (case dependent) | Use is tailored to risk and previous response. |
| Zollinger–Ellison syndrome | Higher or divided doses may be used | Specialist management is typically required. |
Important: If you have been advised to use rabeprazole as part of combination therapy (for example, for H. pylori), the dosing schedule and duration often differ from reflux-only treatment.
Food interactions
Rabeprazole has an important relationship with food timing. In general:
- Best effect: Take before meals, commonly 30 minutes before breakfast.
- After meals: Taking rabeprazole after food may reduce effectiveness because it delays the medicine reaching the active site relative to acid pump activation.
- Consistency with timing: Aim for the same pre-meal routine each day.
Normal meals do not usually “react” with rabeprazole in a harmful way, but timing influences the level of acid suppression you achieve.
Alcohol and medicine interactions
Alcohol
Moderate alcohol may worsen reflux symptoms in some people, even if it does not directly “interact” with rabeprazole. If you experience increased heartburn, regurgitation, or stomach discomfort after drinking, consider reducing or avoiding alcohol while treating reflux or ulcers.
Other medicines (interaction considerations)
Rabeprazole may interact with certain medicines, mainly because acid levels can influence how drugs are absorbed or how liver enzymes process them.
- Medicines affected by stomach pH: Some drugs require stomach acid for best absorption. Acid suppression from PPIs can alter their absorption.
- Antifungals: Certain azole antifungals (e.g., ketoconazole/itraconazole) may have altered absorption when stomach acid is reduced.
- Medicines for blood thinning: If you take anticoagulants (e.g., warfarin), your healthcare professional may monitor INR and overall response when PPIs are used.
- Clopidogrel: Some PPIs can affect clopidogrel activation. The impact with specific PPIs depends on the medicine and guidance. Discuss with a healthcare professional.
- Other medicines metabolised by the liver: PPIs can interact with drugs processed by hepatic pathways. Not every interaction is clinically significant, but it is worth reviewing your full list.
Always tell your pharmacist or doctor about all medicines you take, including:
- Over-the-counter products
- Herbal supplements
- Vitamins/minerals
- Occasional pain relief medicines (especially NSAIDs like ibuprofen/naproxen)
Safety profile: who should take care
Like all medicines, rabeprazole can cause side effects. Most are mild and temporary. However, it’s important to recognise warning signs and discuss concerns with a healthcare professional.
Common side effects
- Headache
- Nausea or stomach discomfort
- Diarrhoea or constipation
- Flatulence (wind)
- Dry mouth or mild dizziness (less common)
Serious but uncommon effects (seek advice urgently)
- Allergic reactions such as swelling of the face/lips, rash, or difficulty breathing
- Severe or persistent abdominal pain
- Vomiting blood or black/tarry stools
- Unexplained weight loss, difficulty swallowing, or persistent vomiting
- Severe dehydration (especially with significant diarrhoea)
- Symptoms of anaemia or marked weakness (especially if long-term use)
Long-term use considerations
PPIs are often used for weeks to months. In some patients, they may be continued longer. Long-term acid suppression can be associated with:
- Vitamin and mineral effects: Low magnesium, and in some cases vitamin B12 deficiency, have been reported with prolonged use.
- Infections: Increased risk of certain gastrointestinal infections (e.g., Clostridioides difficile) has been reported.
- Bone health: Some studies have linked prolonged PPI use with fracture risk, particularly in older adults—this is a risk-benefit discussion.
If you need rabeprazole for an extended period, your healthcare professional may periodically review whether the dose can be reduced or whether step-down therapy is appropriate.
When to seek medical review (important safety notes)
Get prompt medical advice if you have reflux or ulcer symptoms plus any of the following:
- Chest pain that could be cardiac in origin
- Difficulty swallowing or pain with swallowing
- Unintentional weight loss
- Persistent vomiting
- Black stools or blood in vomit
- Symptoms that do not improve after a suitable trial of therapy
These symptoms may indicate conditions that require assessment beyond acid suppression.
Guidance for practical use: maximising benefit
- Use with lifestyle measures: For reflux, consider reducing late-night meals, elevating the head of the bed, and avoiding known triggers (e.g., spicy foods, fatty meals, caffeine for some people).
- Separate from other medicines if needed: If another product requires separation, follow product instructions. For most combinations, careful timing is enough—ask your pharmacist for advice if you take multiple medicines.
- Reassess need: If you are using rabeprazole intermittently or repeatedly, periodic review is helpful to confirm the underlying cause and the best duration.
- Don’t use as “instant relief”: Rabeprazole is not a fast-acting antacid. For sudden breakthrough symptoms, some people use additional short-term relief products as advised by a healthcare professional.
Alternative options (depending on your condition)
Treatment choices depend on diagnosis, severity, and personal factors. Alternatives to rabeprazole may include:
- Other PPIs: e.g., omeprazole, pantoprazole, esomeprazole, lansoprazole (choice depends on response and tolerability)
- H2 receptor antagonists (H2 blockers): e.g., famotidine—may help mild symptoms or intermittent relief
- Antacids: for quick neutralisation of existing acid (short-term symptom relief)
- Alginate-based products: form a foamy barrier to reduce reflux episodes in some people
- Non-medicine strategies: dietary changes, weight management, and addressing contributing factors (like medication-induced reflux)
If symptoms persist despite correct PPI use, it’s important to confirm the diagnosis and consider review for other causes (including non-acid reflux or medication effects).
Market and legal context for Australia
In Australia, medicines are regulated under the Therapeutic Goods Act and listed on the ARTG where applicable. Supply models can vary by product strength and indication. Pharmacy-based products may be available through community pharmacies, with pharmacist guidance on suitability, dosing, and safe use.
Product labelling, Consumer Medicine Information (CMI), and usage instructions are designed to support safe use. If you are unsure which product strength is appropriate, consult a pharmacist and review the pack instructions.
Recent guidance and common clinical considerations
Recent clinical practice across many countries—including Australia—continues to emphasise:
- Right medicine, right dose, right duration: using the lowest effective dose for the shortest effective time, especially for long-term therapy.
- Correct timing before meals: for best symptom control and healing outcomes.
- Review of ongoing need: periodic reassessment for chronic users, considering step-down strategies when appropriate.
- Awareness of safety signals: especially for long-term use (e.g., mineral/vitamin levels, infection risk, and bone health discussions).
Local policies and individual treatment plans can differ. Always follow the product CMI and discuss changes with your pharmacist or doctor.
Delivery, availability, and what to expect from an online pharmacy
Availability can vary depending on brand, strength, and stock levels. When ordering online in Australia, typical steps include:
- Product selection: choose the correct rabeprazole product and strength indicated on the listing.
- Checkout checks: some pharmacies may confirm suitability questions (e.g., allergies, key medical conditions, current medicines).
- Dispatch: many online pharmacies dispatch within business days depending on inventory.
- Delivery: delivery times vary by state and courier service; tracking is commonly provided.
To ensure safe storage, keep rabeprazole in a cool, dry place and follow the package instructions for temperature and moisture protection.
FAQ about rabeprazole (rabeprazole sodium)
1) How quickly does rabeprazole work?
Many people notice symptom improvement within 1–3 days. Full healing of more severe reflux-related injury can take longer (often several weeks), depending on the condition being treated.
2) Should I take rabeprazole with food?
For best effect, take it before food, commonly 30 minutes before breakfast. Taking it after meals may reduce effectiveness.
3) Can I take it with alcohol?
Alcohol doesn’t usually cause a direct dangerous interaction, but it can worsen reflux symptoms for some people. If you notice increased heartburn after alcohol, consider limiting or avoiding it.
4) What if my symptoms come back?
If symptoms return, it may be due to incorrect timing, incomplete course duration, ongoing triggers, or a different underlying cause. Seek advice if symptoms persist or recur frequently.
5) What side effects are most common?
Common side effects include headache, nausea, diarrhoea or constipation, and abdominal discomfort. Most are mild.
6) Is rabeprazole safe for long-term use?
Many people use PPIs for extended periods when benefits outweigh risks. Long-term use should involve periodic review for appropriate dose and duration, and consideration of potential effects such as low magnesium or vitamin B12 in some users.
7) Can I stop rabeprazole suddenly?
Some people may experience rebound acid-related symptoms after stopping. If you’ve been using it long-term, discuss a step-down plan with a pharmacist or doctor.
8) Are there medicines I should avoid?
Several medicines may have clinically relevant interactions depending on the individual (for example, certain drugs affected by stomach pH or liver metabolism). Provide your pharmacist with your full list to check compatibility.
9) Can I use it for occasional heartburn?
Rabeprazole may be suitable for reflux-related symptoms, but occasional heartburn may also respond to lifestyle changes or other short-acting options. Choose based on how frequent and severe symptoms are, and follow the product instructions.
10) When should I seek urgent care?
Seek urgent medical advice for red-flag symptoms such as vomiting blood, black/tarry stools, trouble swallowing, persistent vomiting, severe chest pain, or significant unexplained weight loss.
Disclaimer: This information is intended as a patient guide and does not replace the Consumer Medicine Information or personalised medical advice. If you have questions about suitability, timing, interactions, or side effects, speak with a pharmacist before using rabeprazole.